Sutureless or Stitched Frenuloplasty: Which Technique Suits Which Frenulum
Sutureless frenuloplasty may suit a thin, mildly short frenulum when the surgeon can release it safely without stitches. A thick band, repeated tears, or a visible bleeding vessel may require stitched or V-Y repair. The surgeon chooses the technique after examining tissue thickness, tension, scarring, and bleeding risk, rather than relying on the treatment's name.
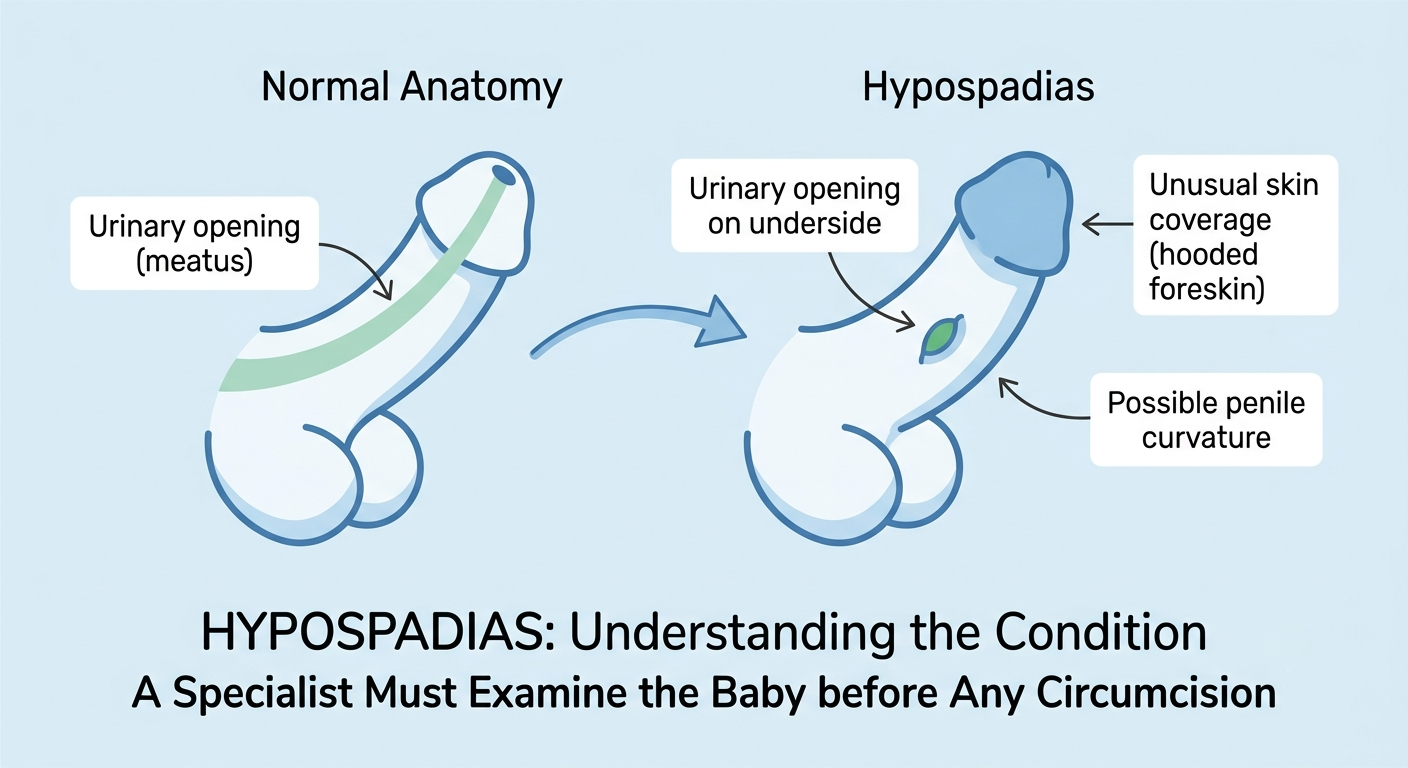
A short penile frenulum can cause pain during erections, discomfort during sexual activity, and repeated tearing beneath the glans. Some men notice bleeding after intercourse, while others experience a pulling sensation whenever the foreskin moves backward.
Frenuloplasty aims to release or lengthen this tight tissue while preserving the foreskin when appropriate.
However, not every patient needs the same surgical technique. Some may qualify for a simple release without stitches, while others require a more controlled repair.
Understanding the differences between sutureless, stitched, and V-Y frenuloplasty can help patients discuss suitable treatment options with their surgeon.
What Is the Difference Between Sutureless, Stitched and V-Y Frenuloplasty?
Frenuloplasty techniques differ in how the surgeon releases tight tissue, controls bleeding, and closes the resulting wound.
Sutureless Frenuloplasty
Sutureless frenuloplasty involves releasing a tight frenulum without placing stitches to close the wound.
The surgeon may use a fine surgical instrument, laser, or electrocautery, depending on the anatomy and available equipment.
This approach may suit selected patients with a thin, mildly short frenulum and limited scar tissue.
However, avoiding stitches does not automatically mean the procedure causes less pain or heals faster. The surgeon must consider bleeding, wound size, and the possibility of scar contraction.
Some patients who initially appear suitable for a sutureless procedure may still require stitches if the surgeon encounters bleeding or tissue tension.
Stitched Frenuloplasty
During frenuloplasty with sutures, the surgeon releases the tight band and closes the tissue using carefully placed stitches.
This technique allows controlled wound closure and may help the surgeon manage bleeding and tissue tension.
Surgeons commonly use absorbable sutures, which gradually dissolve during healing.
A stitched repair may be appropriate for thicker bands, repeated tears, or areas where the surgeon needs greater control over the wound edges.
V-Y Frenuloplasty
V-Y frenuloplasty uses a specific incision and closure pattern to lengthen a tight frenulum.
The surgeon creates a V-shaped incision and rearranges the tissue so that the final closure resembles a Y.
This approach can provide additional length when a simple release may not adequately correct the tension.
However, the surgeon must confirm that the tissue has enough flexibility and blood supply for the planned repair.
Not every thick frenulum requires V-Y surgery. The final decision depends on the individual anatomy.
Which Frenulum Findings Point to Each Technique?
The surgeon should examine the frenulum before recommending treatment.
A thin web of tissue behaves differently from a thick, scarred band. Repeated tearing may also change the tissue and make a simple release less suitable.
The following table provides a practical comparison.
Frenuloplasty Technique Selection Table
| Frenulum Finding | Technique to Consider | Stitches | Typical Healing Considerations | Re-tightening Risk |
|---|---|---|---|---|
| Thin, mildly short web | Sutureless release | May not be needed | Surface healing often takes several weeks | Scar contraction remains possible |
| Thick, tight band | Stitched repair or V-Y | Usually required | Wound closure and tissue tension need monitoring | Depends on the adequacy of lengthening and scar formation |
| Repeated frenulum tears | Stitched or V-Y repair | Often required | Existing scar tissue may complicate healing | May increase if the underlying tension remains |
| Visible bleeding vessel | Controlled release with appropriate bleeding management | May be necessary | Bleeding control takes priority over avoiding stitches | Depends on the final repair |
| Short frenulum with phimosis | Individual assessment for frenuloplasty or circumcision | Depends on procedure | Both the frenulum and foreskin need assessment | Persistent foreskin tightness may require further treatment |
This table provides general educational guidance rather than a fixed surgical rule. Dr. Ashutosh Shah should confirm the final technique selection criteria before publication.
Why Frenulum Thickness Matters
A thin frenulum may allow the surgeon to release the tissue with limited dissection.
A thick band may contain more fibrous tissue and require controlled lengthening.
When the frenulum has torn repeatedly, healing may produce scar tissue that reduces flexibility.
This is why surgeons should assess tissue quality rather than selecting treatment based only on whether a procedure uses a laser or stitches.
Patients experiencing repeated tearing can also read about skin cracks near the frenulum to understand possible causes and treatment considerations.
Does Sutureless Frenuloplasty Mean Faster Healing?
Many patients assume that avoiding stitches automatically produces faster recovery.
However, healing depends on more than the presence or absence of sutures.
Important factors include the size of the wound, tissue thickness, bleeding, infection, movement during recovery, and the amount of tension remaining after the procedure.
A small sutureless release may heal without significant difficulty.
However, an open wound can still develop inflammation, discomfort, or scar contraction.
A stitched repair may initially cause mild tightness or irritation around the sutures, but carefully positioned stitches can support wound alignment.
Neither approach guarantees faster healing.
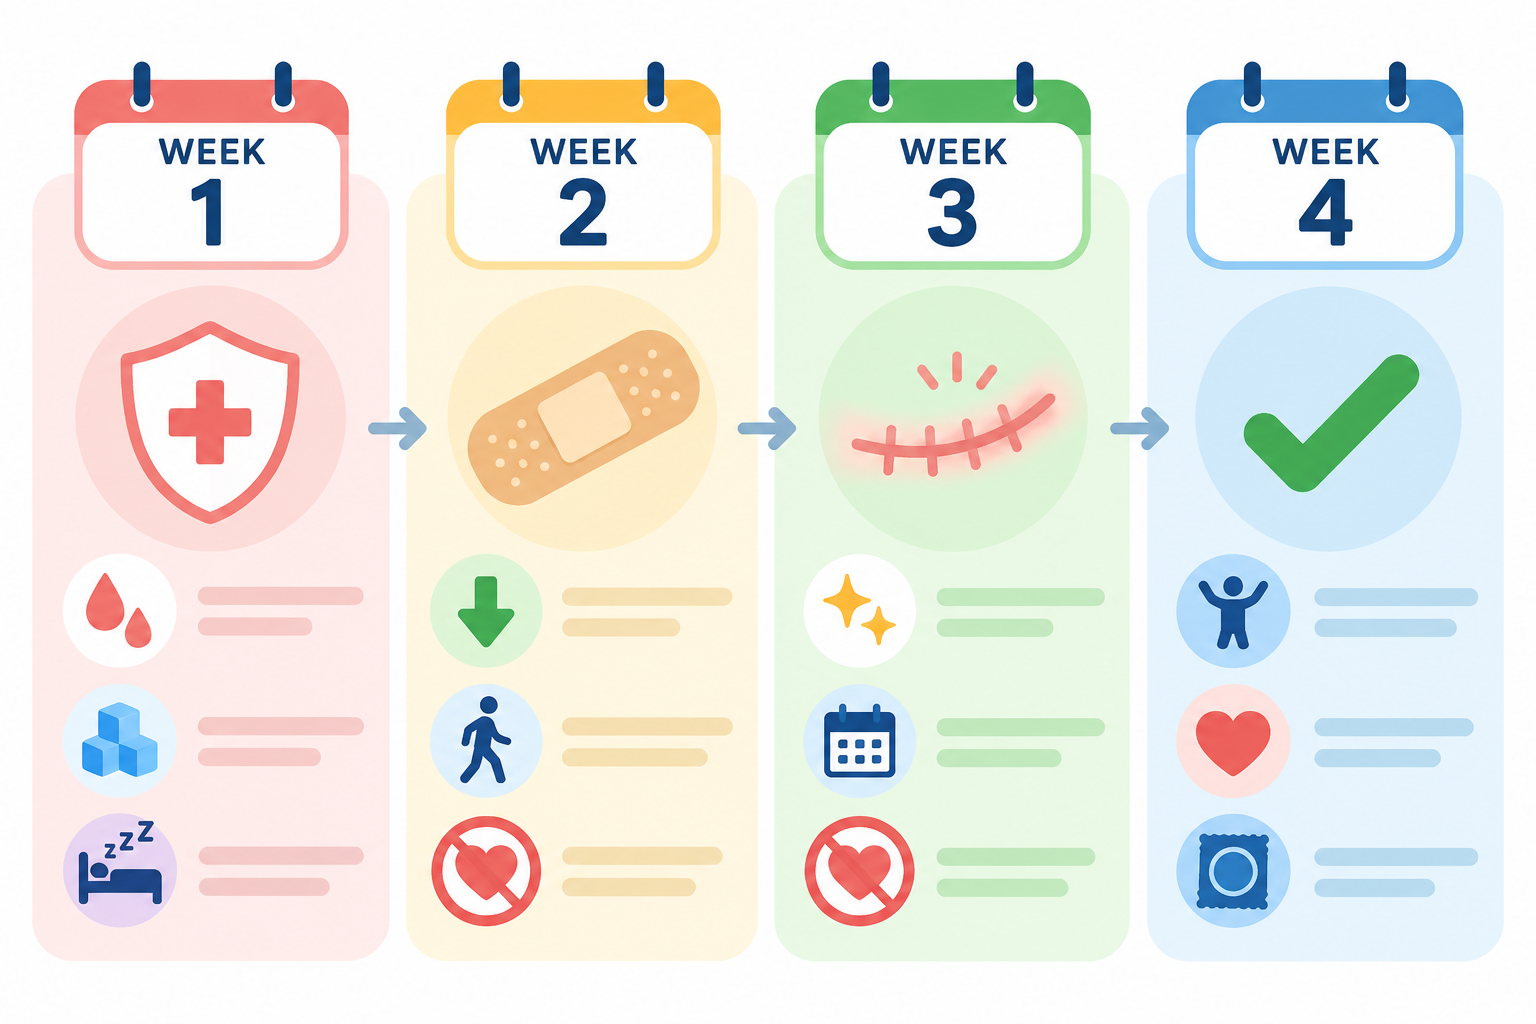
Typical Frenuloplasty Recovery Timeline
| Recovery Period | What Patients May Experience | Recommended Care |
|---|---|---|
| First 48 hours | Mild swelling, tenderness, or spotting | Rest and follow the surgeon's wound care instructions |
| Days 3 to 7 | Gradual reduction in discomfort | Maintain hygiene and avoid friction |
| Week 2 | Continued wound healing; absorbable stitches may begin loosening | Avoid pulling or testing the repaired tissue |
| Weeks 3 to 4 | Improved comfort and further tissue healing | Attend review appointments and follow activity restrictions |
| Weeks 4 to 6 | Many patients approach functional recovery | Resume sexual activity only after the surgeon confirms adequate healing |
Recovery varies between patients. Some wounds take longer to heal, particularly when the surgeon performs a more extensive repair.
Patients can read the detailed frenuloplasty recovery time guide for information about stitches, night erections, and returning to sexual activity.
What Are the Risks of Each Frenuloplasty Technique?
Every surgical technique carries potential risks.
Although frenuloplasty is generally a limited procedure, patients should understand the possible complications before consenting.
Risks of Sutureless Frenuloplasty
A sutureless release may leave a wound that heals without formal closure.
Possible problems include bleeding, delayed healing, infection, discomfort, and scar contraction.
If the surgeon does not achieve sufficient release, the patient may continue experiencing tightness.
A wound that heals with excessive contraction may also produce recurrent pulling.
Risks of Stitched Frenuloplasty
Stitched repair may cause temporary swelling, discomfort, or irritation around the sutures.
Possible complications include infection, wound separation, bleeding, prominent scarring and persistent tightness.
Occasionally, patients develop a small raised area around a healing stitch.
Most absorbable sutures gradually dissolve, but the surgeon may need to assess persistent or irritating suture material.
Risks of V-Y Frenuloplasty
V-Y repair involves tissue rearrangement and therefore requires careful planning.
Potential problems include wound separation, uneven healing, scar sensitivity, changes in sensation, and inadequate lengthening.
A poorly healed repair may leave residual tension or require further evaluation.
Which Technique Has the Lowest Risk?
No single technique has the lowest complication or recurrence rate for every patient.
A simple release may work well for a thin frenulum but may not adequately correct a thick, scarred band.
Similarly, a more extensive repair may offer additional length but also creates a larger surgical wound.
The safest choice depends on the anatomy and the surgeon's assessment.
Frenuloplasty Doctor Near Athwa Surat: How Is the Technique Selected?
Patients considering frenuloplasty should undergo an examination to identify the actual cause of discomfort.
The surgeon checks whether the frenulum is short, thick, scarred, or repeatedly injured.
The assessment may also include foreskin mobility, signs of phimosis, inflammation, and previous tearing.
At Elegance Clinic, Dr. Ashutosh Shah, a Plastic, Reconstructive & Cosmetic Surgeon with over 22 years of surgical experience, evaluates patients with frenulum tightness and related concerns. He considers the tissue condition, symptoms, and available surgical options before recommending an appropriate treatment approach.
During consultation, patients should discuss previous tears, bleeding episodes, discomfort during erections, and any history of foreskin problems.
The surgeon can then explain whether a simple release, stitched repair, V-Y technique, or another treatment may be appropriate.
When Is Circumcision Chosen Instead of Frenuloplasty?
Frenuloplasty and circumcision treat different anatomical problems.
Frenuloplasty primarily addresses a short or tight frenulum.
Circumcision removes the foreskin and may be appropriate when a patient has significant phimosis, recurrent foreskin inflammation, or another condition that requires foreskin removal.
A patient with an isolated short frenulum and otherwise healthy, mobile foreskin may not need circumcision.
However, if both the frenulum and foreskin are tight, correcting only the frenulum may not resolve every symptom.
Patients can compare frenuloplasty or circumcision to understand how surgeons evaluate these options.
For patients with foreskin conditions that may require removal, laser circumcision is another option to discuss with a qualified surgeon.
The use of a laser does not eliminate surgical risks or guarantee a better result.
What Should Patients Know Before Choosing a Technique?
Patients should understand why the surgeon recommends a particular approach.
The decision should consider tissue thickness, scarring, bleeding risk, and the amount of lengthening required.
A patient with mild tightness may benefit from a less extensive procedure, while someone with repeated tears may require a more structured repair.
Patients should also ask whether the surgeon expects to use absorbable stitches, how long recovery may take, and when they can safely resume sexual activity.
It is equally important to understand that frenuloplasty may not completely resolve symptoms when another condition, such as phimosis or skin disease, contributes to discomfort.
For additional information about treatment approaches, read about surgery for a tight frenulum.
The goal isn't simply to avoid stitches. The goal is to safely release the tight tissue while preserving function and minimising complications.
Conclusion: Sutureless or Stitched Frenuloplasty?
Choosing between sutureless frenuloplasty, stitched repair and V-Y frenuloplasty requires more than comparing recovery claims.
A thin, mildly short frenulum may suit a simple release without stitches. A thick band, repeated tears or a wound requiring careful bleeding control may need a stitched or V-Y approach.
However, the surgeon must assess the anatomy before deciding.
Patients should prioritise adequate tissue release, reliable healing and long-term comfort rather than assuming that a stitchless or laser procedure always produces better results.
A qualified surgeon can explain the available options, potential risks and expected recovery based on the patient's individual condition.